The Quinoline Era
1,540 Australian soldiers were given an unregistered antimalarial. 1,157 more got six times the approved mefloquine dose. No follow-up was ever done.

Versión en español: La era de las quinolinas
CASE LOG — ADF Antimalarial Drug Trials, Bougainville & East Timor
TRIAL PERIOD 1998–2002 · SENATE INQUIRY 2018 · ROYAL COMMISSION 2024
I was an army wife. My former husband was deployed to East Timor, where he participated in the antimalarial drug trials this series documents. I lived with the consequences for years before I had the evidence or the framework to understand what had happened — to him, to me, and to our family. This series is the result of that understanding.
THE COHORT — 1,540 ADF personnel received tafenoquine, unregistered for human use anywhere until 2018. A further 1,157 received mefloquine at loading doses up to six times the approved prophylactic dose.
THE FINDING — Vortex keratopathy in 93.2% of tafenoquine recipients examined. Neuropsychiatric adverse events in 13.4%. No longitudinal follow-up has ever been conducted.
Between the late 1990s and the early 2000s, thousands of Australian soldiers were given antimalarial drugs before and during their deployments to East Timor and Bougainville. Many of those soldiers did not know they were participating in clinical drug trials. Some of the drugs they were given had not been approved for use in humans anywhere in the world. Many of the soldiers came home changed — in ways that frightened their families, confused their doctors, and that no institution was equipped to explain or address.
This is the story of how that happened, what it did, and why it has taken more than twenty-five years for any official body to formally acknowledge it.
The drugs
Two compounds sit at the centre of this era. Both were developed by the United States Army. Both belong to the quinoline chemical class — which is where the name "the Quinoline Era" comes from, a term used by veterans, advocates, and researchers to describe this period and its legacy. Both are effective antimalarials. Both carry a neuropsychiatric adverse-effect profile that is now documented in regulatory labelling, peer-reviewed literature, and the testimony of thousands of people who have taken them.
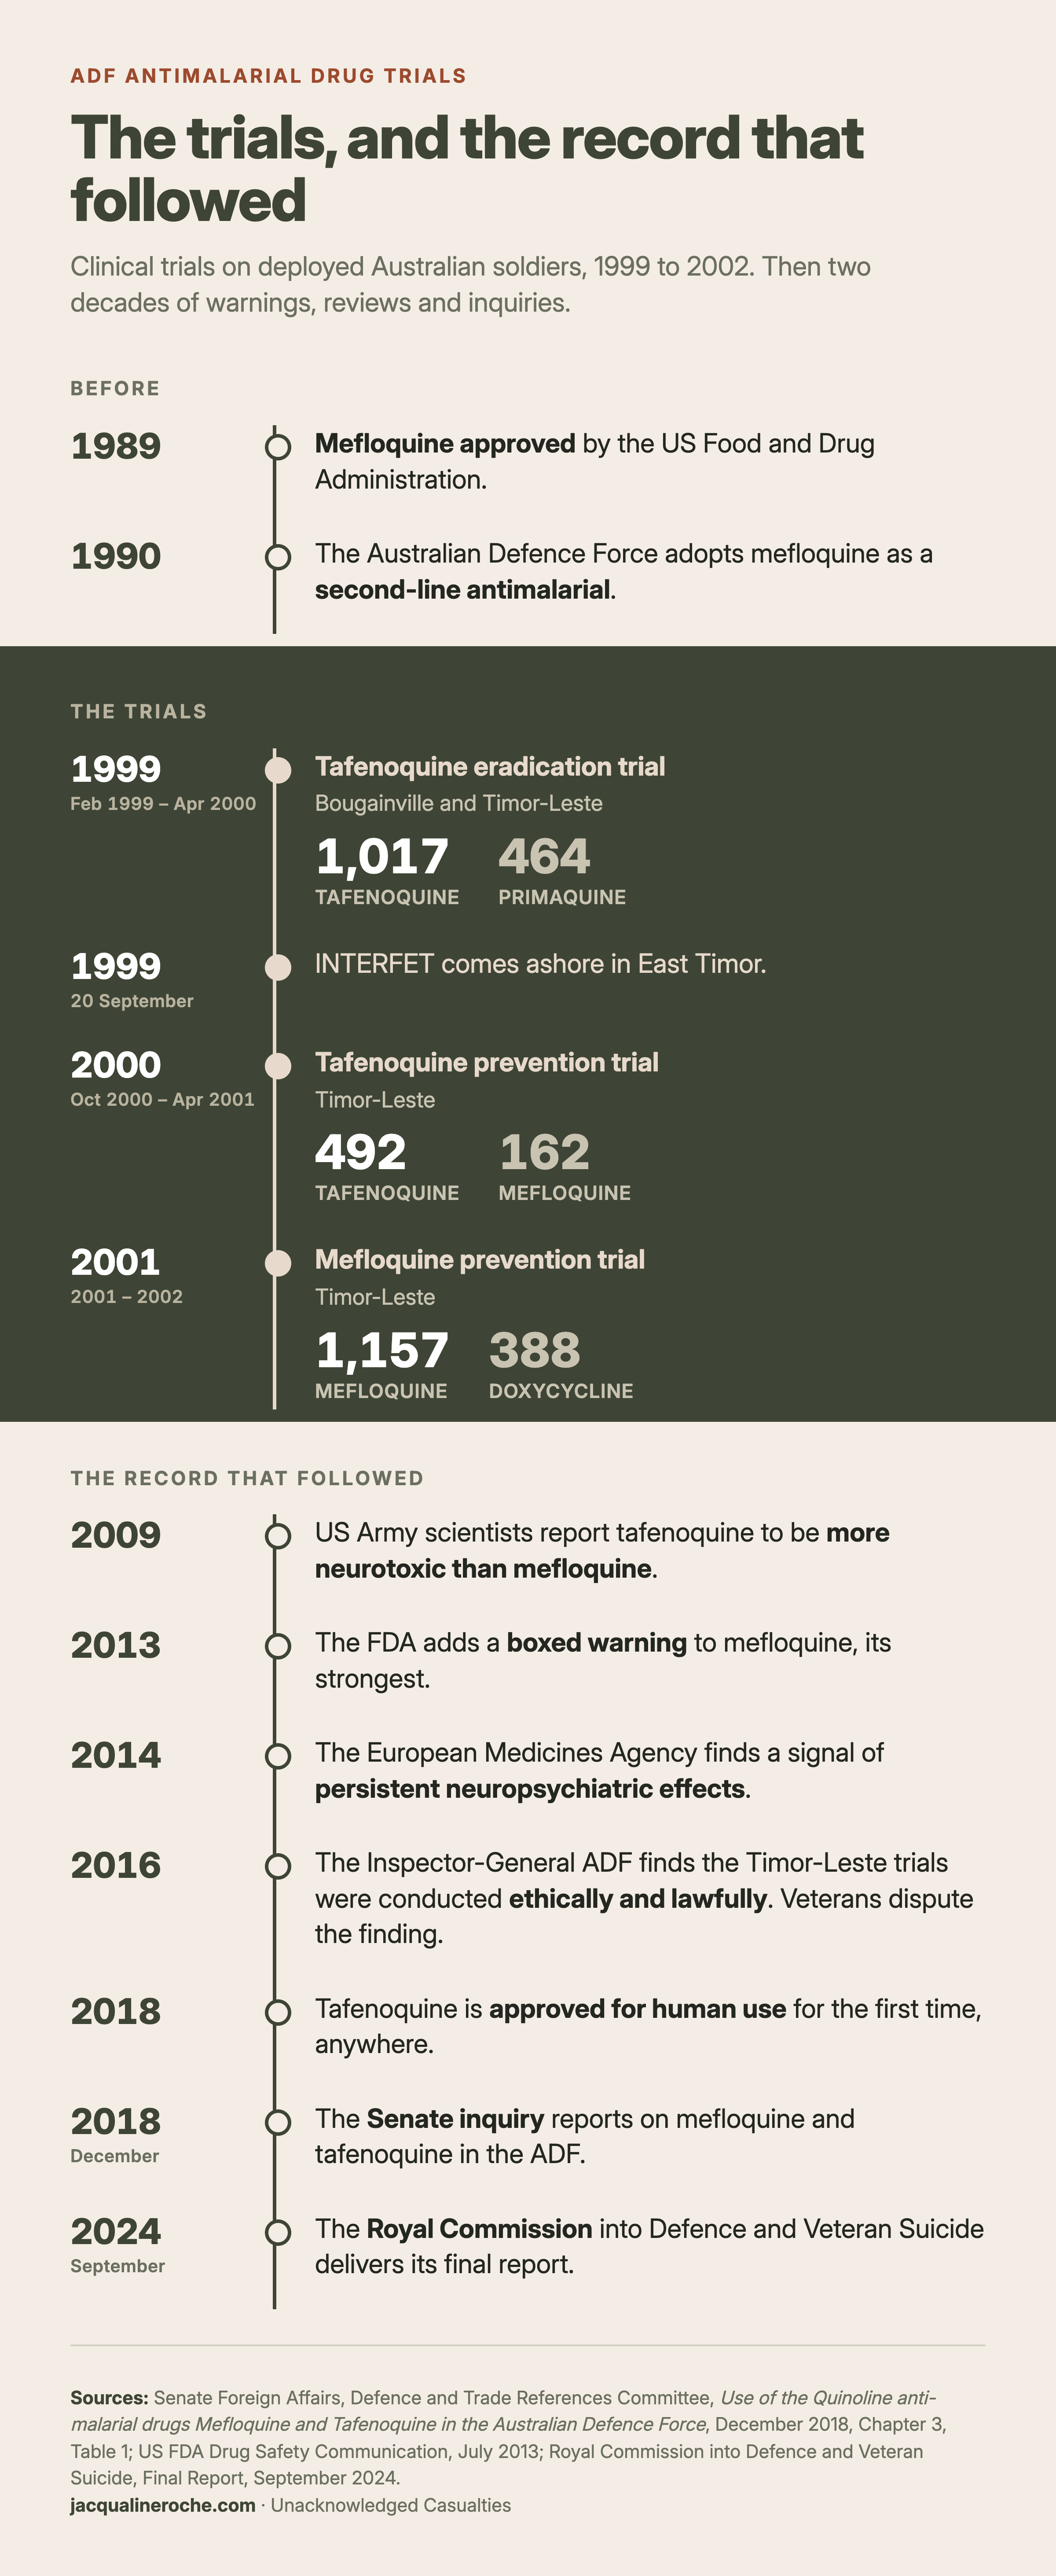
Mefloquine — sold under the brand name Lariam — was developed by the Walter Reed Army Institute of Research in the 1970s and approved by the US Food and Drug Administration in 1989. It was given as a weekly tablet, which made it practical for military use. The Australian Defence Force adopted it as a second-line antimalarial in 1990. Its known adverse effects include nausea, dizziness, insomnia, vivid and terrifying dreams, anxiety, depression, confusion, paranoia, hallucinations, and in some cases psychosis and seizures. In 2013 — more than two decades after it entered military use — the FDA added a boxed warning to the mefloquine label. A boxed warning is the most serious safety alert the FDA issues. It stated that neurological side effects can last for months to years after the drug is stopped, or can be permanent.
Tafenoquine was also developed at Walter Reed, in the 1980s. It was not approved for human use anywhere in the world until 2018. Before that registration, it was trialled on ADF personnel deployed to Bougainville and East Timor between 1998 and 2002, in studies run by the Australian Army Malaria Institute in collaboration with pharmaceutical company GlaxoSmithKline and the US Army medical development program. In 2009, scientists at the Walter Reed Army Institute of Research published findings establishing tafenoquine as the only antimalarial drug more neurotoxic than mefloquine. No longitudinal follow-up health studies were initiated for the 1,540 ADF tafenoquine trial subjects. None have been conducted to this day.
The trials
The Army Malaria Institute was the ADF's dedicated research unit for tropical infectious diseases, based at Gallipoli Barracks in Enoggera, Queensland. Between 1998 and 2002, it ran a series of clinical trials using ADF personnel deployed on active operations as participants.
The trials were funded in part by GlaxoSmithKline and supported logistically by the US Army. This combination — military-run trials, pharmaceutical funding, and service personnel as subjects — created a conflict of interest that advocates, researchers, and ultimately the 2018 Senate inquiry identified as a significant factor in what went wrong.
| Trial | Location | Period | Drug tested (n) | Comparator (n) |
|---|---|---|---|---|
| 1 | Bougainville | 1998–99 | Tafenoquine (378) | Primaquine (214) |
| 2 | East Timor | 1999–2002 | Tafenoquine (636) | Primaquine (289) |
| 3 — Nasveld | East Timor | 2000–01 | Tafenoquine (492) | Mefloquine (162) |
| 4 — Kitchener | East Timor | 2001–02 | Mefloquine (1,157) | Doxycycline (388) |
| 5 — Treatment | Australia | 2000–01 | Tafenoquine (31) | — |
Rows 1–2 follow the trial-by-location breakdown used in this series. The Senate inquiry report, Chapter 3, Table 1 records these as a single 1999–2000 eradication study: 1,017 personnel on tafenoquine and 464 on primaquine (February 1999 – April 2000). See the note on the figures at the end of this article.
The Bougainville trials were among the earliest tests of tafenoquine in a military deployment setting. The drug being tested had not been approved for civilian use anywhere.
The third East Timor trial — known as the Nasveld trial — found vortex keratopathy, a characteristic swirling pattern of deposits on the cornea, in 93.2% of tafenoquine recipients examined ophthalmologically. It also found that neuropsychiatric adverse events were reported in 13.4% of tafenoquine recipients and 11.7% of mefloquine recipients. No neuropsychiatric adverse events from this trial were reported to the Therapeutic Goods Administration at the time. Five adverse event reports were filed for the vortex keratopathy finding — all categorised as "visual impairment."
The fourth trial — the Kitchener trial — found that 57% of mefloquine users reported at least one adverse event, including sleep disturbance in 31% and fatigue in 21%. Three serious neuropsychiatric adverse events were recorded as possibly related to mefloquine. The headline conclusion — that 94% of participants said they would take mefloquine again — was widely cited as evidence of tolerability. The adverse event figures in the same paper received far less attention.
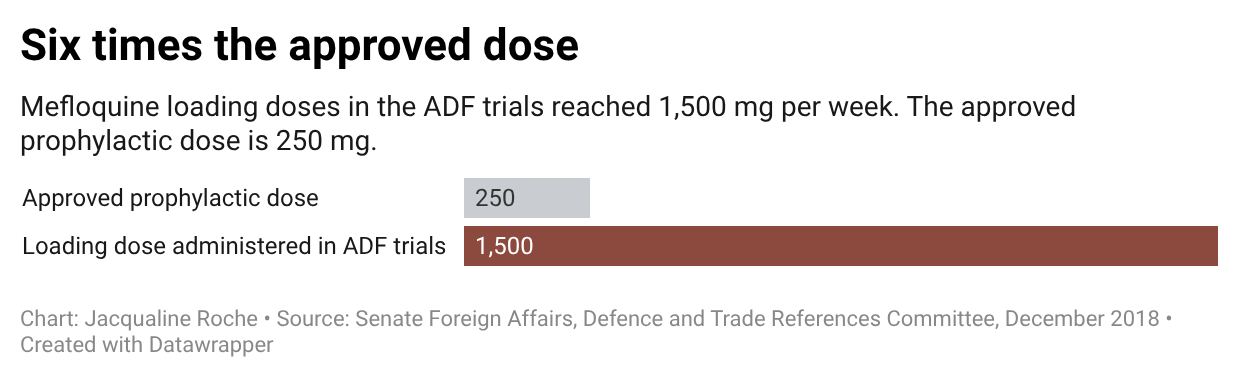
Loading doses of mefloquine in these trials reached up to 1,500 mg per week. The approved prophylactic dose is 250 mg per week. That is six times the approved dose.
What the Senate inquiry found
In 2018, the Foreign Affairs, Defence and Trade References Committee conducted a Senate inquiry into mefloquine and tafenoquine use in the ADF. Its report, tabled in December 2018, identified serious concerns about how the trials had been conducted.
Adverse events were significantly under-reported to the TGA, both during and after the trials. The informed consent process did not adequately disclose the neuropsychiatric risk profile of the drugs, particularly for tafenoquine, which was unregistered at the time. No longitudinal follow-up of trial participants was ever conducted. Veterans who developed symptoms after the trials had no record in their health files connecting their condition to their participation.
The committee accepted that the veterans' symptoms were genuine. It did not make findings on their medical cause, stating that it was not constituted of medical professionals or health experts. Medical experts and organisations giving evidence disagreed with one another on whether the neurological symptoms were caused by the quinoline drugs. The committee also noted an Inspector-General of the ADF investigation which found that the 2000–2002 Timor-Leste trials were conducted ethically and lawfully, that participants consented voluntarily, and that they were adequately informed of the side effects known at the time — findings that affected veterans and their advocates dispute, and which the committee declined to reopen.
The inquiry made fourteen formal recommendations addressing research ethics reform, claims pathways, clinical guidelines, and a neurocognitive health program. The government agreed to twelve and agreed in principle to the remaining two. The health assessment program that followed was contracted to Bupa without a public tender process. It delivered 109 assessments against a cohort of thousands. The contract was subsequently referred to the National Anti-Corruption Commission.
What the Royal Commission found
The Royal Commission into Defence and Veteran Suicide delivered its final report in September 2024. Volume 4, Chapter 22 addressed mefloquine and tafenoquine directly. It was the first time an Australian body at that level had accepted the framework of brain injury — rather than psychiatric disorder — as the appropriate lens for this population.
Recommendation 61 called for a dedicated brain-injury program for veterans exposed to mefloquine and tafenoquine. The Australian Government agreed to the recommendation in principle in December 2024 and referred it to a taskforce for further advice.
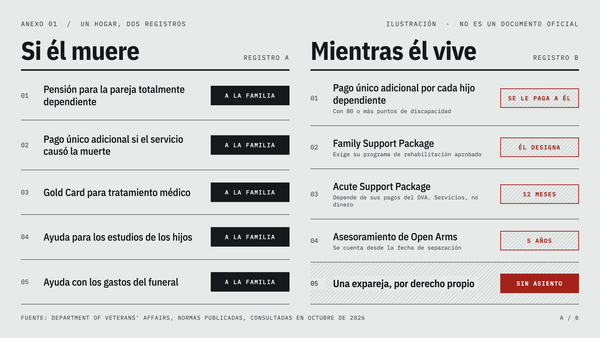
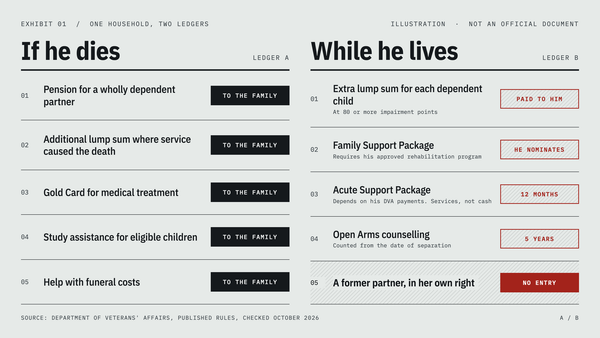
The families of affected veterans — the spouses, partners, and children who lived with the consequences — are outside the scope of that program. No policy pathway exists for them. No research has been commissioned to document their situation. No apology has been made.
Why it matters now
The Quinoline Era is not a historical episode. It is an ongoing one. Veterans are still living with neurological injuries that have never been correctly diagnosed or treated. Partners and former partners are still living with the consequences of behaviour that was never correctly explained. Adult children are still making sense of childhoods that no institution has ever formally acknowledged.
The evidence that would have justified a faster, more complete response has existed in the peer-reviewed literature, the regulatory record, and the advocacy submissions for decades. The 2013 FDA boxed warning on mefloquine preceded the Australian Senate inquiry by five years. The 2014 European Medicines Agency finding on persistent neuropsychiatric and vestibular effects from mefloquine preceded it by four years.
What has been missing is not evidence. What has been missing is the institutional willingness to act on it — and the public visibility that creates the pressure for institutions to do so.
Unacknowledged Casualties is an attempt to contribute to that visibility. The other articles in the series examine what the drugs did to the brain, what that looked like inside a household, and what it cost the people who lived there.
Key sources
- Senate Inquiry report and submissions, December 2018 — Parliament of Australia. Particularly Submission 94 (McCarthy) and Submission 16 (Australian Quinoline Veterans and Families Association, including Professor Quinn's evidence).
- Royal Commission into Defence and Veteran Suicide, Final Report, Volume 4, Chapter 22, September 2024.
- US Food and Drug Administration Drug Safety Communication on mefloquine, July 2013.
- European Medicines Agency PRAC Assessment Report EMA/63963/2014. Not published online by the EMA; cited in Nevin RL (2017), Pharmacology Research & Perspectives.
- Repatriation Medical Authority investigation record, August 2017.
- Specialist Medical Review Council decision, September 2018.
- Peer-reviewed literature includes Ritchie, Block and Nevin (2013); Nevin (2014, 2016); Quinn (2015); McCarthy (2015); Nasveld et al. (2010); Kitchener et al. (2005).
Note on the figures
The trial numbers in this series come from the Department of Defence's own record of the Army Malaria Institute studies, as reproduced in the 2018 Senate inquiry report.
- Tafenoquine: 1,540 personnel. 1,017 in the 1999–2000 eradication study (Bougainville and Timor-Leste), 492 in the 2000–01 prevention study (Timor-Leste), and 31 in a 2000–01 treatment study in Australia.
- Mefloquine in the trials: 1,319 personnel. 1,157 in the 2001–02 prevention study (Timor-Leste), and 162 in the comparator group of the 2000–01 tafenoquine prevention study.
- Tafenoquine or mefloquine in the trials: up to 2,859 personnel (1,540 + 1,319), described in this series as "nearly 3,000". Some people may have taken part in more than one study.
- All trial participants: 3,711, including the comparator groups given primaquine (464) or doxycycline (388).
- 3,523 is a wider figure. The Senate committee's maximum combines everyone who took either drug in the studies with mefloquine prescribed to ADF members outside the studies since 2001. The committee noted it is "likely" an overestimate because the groups may overlap.
Sources
- Senate Foreign Affairs, Defence and Trade References Committee, Use of the Quinoline anti-malarial drugs Mefloquine and Tafenoquine in the Australian Defence Force, Chapter 3, December 2018 — paragraphs 3.28–3.29 and Table 1.
- Department of Defence, Antimalarial medications — trial participant numbers by study.
Related reading
- Next in the series: About This Series
- One Tablet
- What the Record Would Not Hold
- The ADF Antimalarial Drug Trials: A Timeline
Part of Unacknowledged Casualties. Read the full series at /unacknowledged-casualties/
Correction, 5 October 2026: This article originally said the Government accepted Recommendation 61 in December 2024. The Government’s published response was “agree-in-principle”, with the recommendation referred to a taskforce. The sentence has been corrected.